Migraines That Started After Something: Tracing the Trigger Back | Atlas Chiropractic

Headache intake forms ask what sets one off. Food, weather, sleep, hormones, stress. What almost nobody asks is when the headaches started and what was happening that year. Patients at Atlas Chiropractic in Fort Wayne usually answer that second question immediately once someone asks, and the answer is often a specific event: a rear-end collision, a fall on ice, a season of high school football, a delivery that required intervention. Headaches that began after something are a different picture than headaches that simply appeared.

Why does the onset story matter more than the trigger list?

Triggers describe what provokes an episode. Onset describes what created the susceptibility. Only one of those points toward a cause.

Someone whose migraines began in adolescence with a family history is describing a primary headache disorder. Someone whose headaches began four months after a car accident, having never had them before, is describing something else. The International Classification of Headache Disorders, now in its third edition from the International Headache Society, maintains whole categories for headaches attributed to trauma or injury to the head and neck for this reason.

What counts as an onset event?

Any force that loaded the head and neck, including ones that seemed minor at the time. People routinely dismiss the incident because they were not hospitalized.

Worth listing on paper: collisions of any speed, falls onto ice or stairs, sports impacts, a birth involving forceps or vacuum extraction, a hard fall in childhood, prolonged dental work with the jaw held open, surgery involving intubation and head positioning. The gap between events and symptoms is often long. Patients commonly report months or years, which is part of why the connection gets missed by everyone including the patient.

Is it a migraine or a cervicogenic headache?

a man having a headache

Cervicogenic headache is head pain referred from a structural problem in the neck, classified separately from migraine in the ICHD criteria. The two overlap enough that misclassification is common.

Features leaning cervicogenic include pain that stays on one side without switching between episodes, onset at the base of the skull spreading toward the eye or temple, provocation by sustained neck positions or specific movements, reduced rotation to one side, and tenderness over the upper cervical joints. Nausea and light sensitivity occur with both, so those do not settle the question.

Why would a neck problem cause pain behind your eye?

Because of convergence in the brainstem. Sensory fibers from the upper cervical nerve roots and fibers from the trigeminal nerve, which supplies the face and front of the head, terminate in the same region.

The nervous system cannot always tell which input produced a signal arriving on a shared pathway, so an irritated joint at C1 or C2 gets felt in the forehead, temple, or behind the eye. That anatomy, described in research on the trigeminocervical complex by Bartsch, Goadsby and others, is the accepted explanation for why neck structures refer pain into the head at all.

Doesn’t almost everyone with migraine have neck pain?

Yes, and that is the real complication. Neck pain is common during migraine attacks and often appears in the hours before one starts, as part of the attack rather than its cause.

Neck symptoms alone prove nothing. What raises the question is the combination: a clear onset event, a side that does not change, restricted neck movement between episodes, and pain reproducible by position rather than only by the usual triggers.

How do you trace your own timeline?

Write it down before your next appointment. Memory reorganizes itself around symptoms and loses the ordinary events that preceded them.

Put down the year and, if possible, the month they began. List everything physical that happened in the eighteen months before, including incidents you walked away from. Note whether the side has ever switched. Track duration, location, and what position you were in when one started. A pattern that seems random in your head often resolves into something specific on paper.

What does Atlas Chiropractic examine?

Mechanism first, then measurement. The history focuses on how force entered the body and when symptoms followed, and the exam looks for objective, repeatable findings rather than impressions.

The NUCCA protocol, from the National Upper Cervical Chiropractic Association, uses precision imaging with the head set to a defined reference to quantify atlas position in degrees, alongside a supine leg check, postural assessment, and cervical range of motion. Follow-up imaging confirms whether the correction changed that measurement.

Some headaches need a physician urgently. Sudden severe onset, new headaches after age fifty, fever with a stiff neck, neurological changes, or a steadily worsening pattern all require medical evaluation first.

The question nobody asked may be the useful one. Atlas Chiropractic takes headache histories back to their starting point for Fort Wayne patients and evaluates the upper cervical spine when the timeline points there. Reach out through the site if your headaches begin after something. This page is educational and does not replace evaluation by your physician.


Text Neck Isn’t the Problem. Why Your Head Can’t Sit Level Is. | Atlas Chiropractic

Sit up straight. Raise your monitor. Put the phone at eye level. Most people have heard it, tried it, and found the ache returns the moment they stop thinking about it. Patients bring that frustration to Atlas Chiropractic in Fort Wayne as a confession, as though the problem were willpower. It usually is not. Posture you maintain by effort is not posture. It is a temporary override of whatever your nervous system has settled on, and the setting underneath is what deserves examining.

Does text neck actually cause neck pain?

a woman suffering from neck pain

The evidence is weaker than the term suggests. Several studies looking specifically at this question have not found the association people assume exists.

A 2018 study by Damasceno and colleagues in the European Spine Journal examined text neck and neck pain in young adults and reported no meaningful relationship. Research on adolescent posture clusters, including work by Richards and colleagues, found that how someone habitually sits did not cleanly predict who developed neck pain. Plenty of people with terrible screen habits have no symptoms, and plenty with careful ergonomics hurt daily.

Where did the sixty-pound figure come from?

A 2014 calculation by a spine surgeon, Kenneth Hansraj, published in Surgical Technology International, modeling the load on the cervical spine at various angles of forward head flexion.

It circulated everywhere. It was also a computer model rather than a measurement in living people, and it has drawn methodological criticism since. Loading the neck more at sixty degrees of flexion than at zero is real physics. Concluding from that model that phone use causes a clinical condition goes well beyond what it showed.

Why doesn’t sitting up straight fix anything?

Because resting posture is regulated below conscious control. You can hold a corrected position for as long as you pay attention to it, and attention is a limited resource.

Postural tone is set by reflex systems constantly integrating input from the inner ear, the eyes, and position receptors in the deep muscles of the neck. Those systems have a default they return to the instant you stop overriding them. If the default is asymmetric, effort produces a temporarily better-looking posture and no change to the underlying pattern.

What does it mean that your head cannot sit level?

The nervous system prioritizes keeping your eyes and inner ear level with the horizon. When something at the top of the neck prevents that, the body compensates lower down to restore the horizon.

That is where forward head posture, a dropped shoulder, a hiked hip, and a functional leg length difference come from. They are the adaptation, not the fault. Your head weighs roughly ten to twelve pounds and balances on the atlas, a ring of bone weighing about two ounces, with no disc above or below it. When that joint sits off neutral, everything beneath adjusts to keep your gaze level, and the compensation shows up as the posture people keep trying to correct.

How can you tell if your head is tilted?

Look for asymmetry that persists rather than posture that looks slumped. Slumping is a load problem. Asymmetry is a structural one.

  • Eyeglasses that sit crooked no matter how often they are adjusted
  • One ear visibly higher than the other in a straight-on photo
  • A shirt collar or hemline that rides up on one side
  • One shoulder consistently lower, noticeable in photos more than in a mirror
  • Shoe soles wearing unevenly between left and right
  • Sleeping comfortably only on one side

Any single item means little. A pattern across several is worth measuring.

What does Atlas Chiropractic measure instead?

Position, quantified. The NUCCA protocol, from the National Upper Cervical Chiropractic Association, uses precision imaging with the head set to a defined reference, then measures the relationship between the skull, the atlas, and the vertebra below in degrees.

The exam adds findings that can be repeated at every visit: a supine leg check for functional length difference, shoulder and hip level, head rotation. Misalignments here are usually small, often a few degrees. Small numbers matter at the one joint carrying the entire weight of the head, where the density of position receptors is among the highest in the body.

So is ergonomic advice worthless?

No, but it belongs in a different category. Screen height, breaks, and movement manage load. They do not correct alignment.

Getting up every twenty to thirty minutes, bringing the screen to eye level, and supporting your forearms all reduce sustained strain, which genuinely helps symptoms. Treat that as maintenance rather than as the cure that failed you.

Blaming your phone puts the responsibility somewhere it cannot be fixed by effort. Atlas Chiropractic evaluates why the head is not sitting level for Fort Wayne patients, using measurement rather than posture coaching. Reach out through the site if you have been correcting your posture for years and the symptoms have not moved. This page is educational and does not replace evaluation by your physician.

Your X-Rays Are Normal. Why Does Your Neck Still Hurt? | Atlas Chiropractic

You waited three weeks for the appointment, got the films, and heard the word normal. Then you drove home with the same headache you came in with. Patients arrive at Atlas Chiropractic in Fort Wayne carrying that exact report, half convinced they are imagining the problem. They are not. A normal radiology read answers one question very well, and it is not the question you came in with.

What is a radiologist actually looking for?

people looking at an x-ray

Pathology that needs medical or surgical attention. Fractures, dislocations, tumors, infection, significant instability, and advanced degenerative disease.

Those are the right things to check, and finding none of them is genuinely good news. A standard cervical series is a rule-out study. It is designed to answer whether something dangerous is present, not to characterize how your head is sitting on your spine or whether a joint is functioning. Normal means nothing alarming appeared. It does not mean nothing is wrong.

Why do imaging findings match symptoms so poorly?

Because degeneration and pain track each other loosely in both directions. Plenty of people with dramatic films have no symptoms, and plenty with clean films hurt considerably.

A systematic review by Brinjikji and colleagues in the American Journal of Neuroradiology in 2015 found spine degeneration on imaging in a large share of people with no symptoms at all, with prevalence climbing by decade. Cervical MRI research on healthy volunteers, including a 2015 study by Nakashima and colleagues in Spine, found disc bulging in the large majority of asymptomatic subjects. Findings on a film are common enough that their presence explains less than patients assume, and their absence rules out less than it seems to.

What does a standard neck X-ray not show?

Soft tissue and function. Plain radiographs image bone, in two dimensions, with the patient holding still.

Ligaments, facet capsules, and the deep suboccipital muscles do not appear. Neither does what happens when you turn your head. The upper cervical region is also hard to visualize on routine views, since the jaw and skull base overlap the atlas and axis, which is why a dedicated open-mouth view exists and is not always part of a standard series. A joint can be misaligned by a few degrees and stay invisible on a film never positioned or measured to detect it.

How does Atlas Chiropractic image the neck differently?

By measuring rather than reading. The NUCCA protocol, from the National Upper Cervical Chiropractic Association, uses a specific series of precision views with the head positioned to a set reference, then applies line drawing and angular measurement to produce actual numbers.

The frontal, lateral, and overhead views together describe how the atlas sits relative to the skull above and the axis below. Misalignments are typically small, often only a few degrees, which is why they do not announce themselves on a general screening film. Those numbers set the direction and force of the correction, and follow-up imaging verifies whether the measurement changed.

What does that change about the appointment?

It replaces interpretation with a number you can compare against later. Rather than assessing whether an adjustment felt effective, there is a before value and an after value.

The same logic applies to the exam itself. A supine leg check showing a functional length difference, postural asymmetry at the shoulders and hips, and restricted head rotation are objective findings that can be re-measured at every visit.

Why does the pain show up somewhere other than the problem?

Because the upper cervical nerves converge with the trigeminal nerve in the brainstem, so irritation at the base of the skull frequently gets felt in the forehead, the temple, or behind the eye.

That referral pattern is why someone with an upper cervical issue may report headaches and jaw tension while insisting their neck feels fine. It also explains why imaging aimed at the painful area comes back clean. The films were pointed at the destination rather than the origin.

When is a normal X-ray still the most important result you can get?

When you have red flags. Trauma, unexplained weight loss, fever, night pain that wakes you, progressive weakness, numbness, or changes in bowel or bladder function all require medical evaluation, and clean imaging in those situations is exactly what you want.

That clearance also comes first for any manual care of the upper neck. Ruling out fracture and instability is not a formality. It determines whether hands-on work is appropriate at all.

Clean films mean the dangerous possibilities were excluded, which is the starting point of an answer rather than the end of one. Atlas Chiropractic evaluates the upper cervical spine for Fort Wayne patients using precision imaging and measurement, looking at position and function rather than screening for pathology alone. Reach out through the site if your report said normal and your symptoms disagree. This page is educational and does not replace evaluation by your physician.

Post-Concussion Symptoms That Won’t Resolve: The Craniocervical Junction Connection | Atlas Chiropractic

The hit happened in September. It is February and the headaches are still there, along with the fog, the afternoon fatigue, and the sense that bright rooms are too much. Every scan came back clean. Atlas Chiropractic sees this in Fort Wayne often enough to ask a question most patients never get asked: what happened to your neck when your head got hit? The brain did not absorb that force alone, and the joint where your skull meets your spine is often the part nobody examined.

How long should concussion symptoms normally last?

a lady with an injured neck

Most resolve within two to four weeks. The 6th International Consensus Statement on Concussion in Sport, published in 2023 following the Amsterdam meeting, defines persisting symptoms as those continuing beyond four weeks.

Somewhere between 10 and 30 percent of people cross that line, depending on the study population. Once you are months out, the question shifts. A brain injury that was going to heal on its own timeline usually has. Something is still generating symptoms, and it is worth finding out what.

Why does a neck injury get missed after a concussion?

Because the symptom lists are nearly identical. Whiplash and concussion both produce headache, dizziness, brain fog, fatigue, light sensitivity, and trouble concentrating.

When a patient arrives with a documented head impact, the evaluation reasonably focuses on the brain. Reviews of the cervical spine’s role in post-concussion syndrome, including work by Marshall and colleagues, point out the obvious physics: no force sufficient to concuss the brain reaches it without passing through the neck. Both injuries happen. Only one tends to get named.

What is the craniocervical junction?

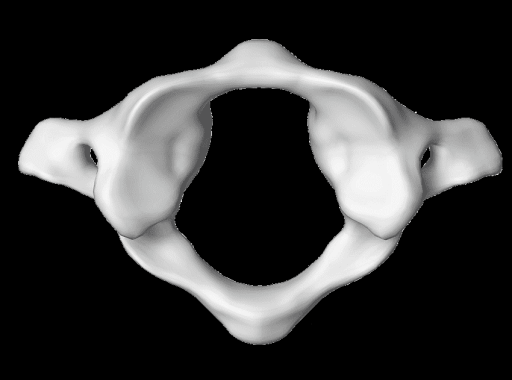
It is the transition where the skull meets the top of the spine, made up of the occiput, the atlas (C1), and the axis (C2). It is the most mobile and least mechanically stable region of the spine.

The deep suboccipital muscles carry one of the highest densities of muscle spindles in the body. Those receptors feed positional information into the same systems handling balance and vision, and the upper cervical nerve roots converge with the trigeminal nerve in the brainstem, which is why an irritated joint at the base of the skull refers to pain in the forehead and behind the eyes. Disturb the input from that region and the output looks like dizziness, headache, and visual strain.

Which symptoms suggest the neck is involved?

Symptoms tied to head position and neck movement rather than to cognitive exertion alone. A few patterns show up repeatedly:

  • Headache starting at the base of the skull and traveling forward, often on one side
  • Dizziness provoked by turning or holding the head, rather than by rolling over in bed, which points more toward an inner ear cause
  • Symptoms that worsen after sustained desk or screen posture
  • Persistent neck stiffness or a sense that the head does not sit level
  • Jaw tension or clicking that appeared around the same time

None of these confirms anything on its own. Together they are worth an examination of the region.

Does research support addressing the cervical spine?

There is meaningful evidence, though the literature is still developing. A randomized controlled trial by Schneider and colleagues published in the British Journal of Sports Medicine in 2014 studied athletes with symptoms persisting more than ten days and found substantially higher rates of medical clearance within eight weeks among those receiving cervical spine and vestibular treatment compared to controls.

That trial was small, which is typical of this field. The cervical contribution to persisting symptoms is recognized in sports medicine and increasingly built into rehabilitation protocols. Promising outcomes is a different matter, and any practitioner who does should give you pause.

What does Atlas Chiropractic do differently?

NUCCA work is measurement-driven. The National Upper Cervical Chiropractic Association protocol uses precision imaging to quantify a misalignment in degrees, then applies a low-force correction by hand with no twisting, popping, or sudden movement of the neck.

Follow-up imaging verifies whether the correction changed the measurement rather than relying on how it felt. For someone whose symptoms began with trauma, that distinction matters. Guessing is not an acceptable approach to an injured upper neck.

What has to be ruled out first?

Fracture and ligamentous instability. Anyone with a recent head or neck injury needs medical evaluation before any manual care, and appropriate imaging comes before anyone touches the region.

Upper cervical instability is a contraindication, not a treatment target. A thorough history covering the mechanism of injury, prior trauma, and red flag symptoms is part of a legitimate evaluation.

Persisting symptoms months after a head injury deserve a look at the structure that took the same force the brain did. Atlas Chiropractic evaluates the craniocervical junction for Fort Wayne patients whose post-concussion symptoms have not resolved, using imaging and measurement rather than assumption. Reach out through the site to discuss whether an upper cervical evaluation makes sense for your situation. This page is educational and does not replace evaluation by your physician.
Winter in Fort Wayne: How Icy Falls and Snow Shoveling Stress Your Upper Cervical Spine

Fort Wayne averages around 30 inches of snow in a typical winter, and the injuries arriving at Atlas Chiropractic between December and March follow a predictable pattern. Someone slips in a driveway, catches themselves, walks away thinking nothing happened, then calls three weeks later about headaches that will not quit. The connection is not obvious, which is exactly why it gets missed.

Why does a fall on ice affect your neck even when you land on your hip?

Because your head keeps moving after the rest of you stops. Landing on a hip, an elbow, or a tailbone sends force up through the spine while the head, weighing roughly 10 to 12 pounds, travels along its original path a fraction of a second longer. The tissue absorbing that mismatch is the ligament and joint capsule around the atlas and axis, the top two vertebrae of the neck (C1 and C2).

The atlas itself is a ring of bone weighing about two ounces, and it serves as the balance point for the entire head. It does not take a dramatic impact to shift it out of the position it was built to hold. This is the same acceleration and deceleration mechanism people associate with rear-end car collisions, produced at low speed by a patch of black ice.

How often does snow shoveling actually hurt people?

More often than most people assume. Research by Watson, Shields, and Smith published in the American Journal of Emergency Medicine in 2011 examined US emergency department records from 1990 through 2006 and found roughly 195,000 snow shovel related injuries and medical emergencies, averaging about 11,500 a year.

Soft tissue injuries were the most common outcome, and the lower back was the single most frequently injured region. Acute musculoskeletal exertion accounted for slightly more than half of all cases, slips and falls for about one in five. Cardiac events made up a small share of injuries but accounted for every fatality in the dataset.

Person shoveling snow from a handicapped parking space near a park bench in winter.

What symptoms show up after a winter fall, and how long do they take?

Upper cervical symptoms after a fall commonly appear 24 to 72 hours later rather than immediately, because inflammation and protective muscle spasm build over the first day or two. That delay is why people disconnect the two events.

What to watch for in the days after a slip:

  • A headache that starts at the base of the skull and wraps forward
  • Neck stiffness that is worse in the morning than at night
  • Dizziness or a brief off-balance feeling when standing or turning your head
  • One shoulder or hip sitting visibly higher than the other
  • Jaw tightness, ear fullness, or ringing on one side
  • Old aches from a previous injury returning without explanation

Any of those appearing within a week of a fall is worth an examination even if the fall felt minor at the time.

How should you shovel to protect your neck and back?

Push the snow rather than lifting it whenever your driveway allows, and pivot your feet instead of twisting your spine to throw. A shovelful of wet Indiana snow can run 15 to 20 pounds, and a forward-bent neck plus a loaded lift plus a rotational throw stacks three stresses on the same segments.

Specifics that hold up in practice:

  • Warm up for five to ten minutes before you start, even just walking indoors
  • Clear in two-inch layers during heavy snowfall rather than waiting and moving the full depth at once
  • Alternate which side you throw to, and switch your grip periodically
  • Break every ten to fifteen minutes, and drink water despite not feeling thirsty
  • Use a bent-shaft shovel sized so you are not bending your neck to see the blade
  • Keep your head up while you work rather than staring down at the pavement

Sidewalks in Fort Wayne are the responsibility of the adjacent property owner, so plan for the pace of clearing rather than rushing a large area before work.

When is a winter fall a medical emergency instead of a chiropractic visit?

Some situations need a physician or an emergency department first. Seek emergency care for loss of consciousness, confusion, repeated vomiting, vision changes, weakness or numbness in an arm or leg, or a head strike in anyone taking a blood thinner, whether or not they feel fine afterward. Suspected fracture, severe unremitting neck pain, and inability to bear weight also belong in a medical setting before manual care.

The American Heart Association advises people with known heart disease or significant risk factors to avoid shoveling altogether. Chest pressure, jaw or arm pain, or unusual shortness of breath while clearing snow means stopping and calling for emergency help, not finishing the driveway.

Getting checked after a fall at Atlas Chiropractic

A winter slip does not have to become a spring headache. Upper cervical care measures whether the atlas actually shifted rather than guessing from how your neck feels, which matters most for the falls that seemed too small to bother mentioning. If you went down on the ice this season, schedule an examination with Atlas Chiropractic and find out what your spine absorbed.


Why NUCCA Patients Don’t Need Constant Adjustments: Understanding How You “Hold” Your Correction

If you have spent years getting adjusted at every visit, the approach at Atlas Chiropractic can feel odd at first. You show up, the doctor runs a series of tests, and then says you do not need anything done today. That is not a wasted trip. In NUCCA care, you get an adjustment because measurements say you need one, and the whole point of the first phase of care is reaching a stage where you need it less and less.

What does it mean to “hold” your correction?

Holding means the atlas, the top vertebra of your neck (also called C1), has stayed in its corrected position since your last visit, and the rest of your body has stayed balanced with it. NUCCA stands for the National Upper Cervical Chiropractic Association, and the technique treats the correction as the goal while the adjustment is only the tool used to get there. Once the tool has done its job, using it again works against you.

The atlas is a thin ring of bone weighing about two ounces that balances a head of roughly 10 to 12 pounds. Sitting at the very top of the spine, a misalignment of even a couple of degrees changes how the head rides over the shoulders, how the pelvis levels out, and how the postural muscles fire to keep you upright. Correct that ring and the compensations underneath it release. Keep it where it belongs and they stay released.

Why doesn’t every NUCCA visit include an adjustment?

Adjusting a joint that is already in the right place adds motion to a segment you are trying to make stable. Repeated force through healing ligaments can loosen them, which makes the next misalignment easier to produce and harder to keep out. That is the core reason your doctor may check you, find you balanced, and send you home.

If you are adjusted every visit regardless of your findings, neither you nor the doctor ever learns how long your body can maintain the correction on its own. That number determines how far apart your visits can safely be spaced, which makes it one of the more useful pieces of information in your file.

How does the doctor know whether you’re holding?

The determination is made with objective tests before anything is touched. A standard NUCCA re-examination includes a supine leg length check, where a functional difference of a quarter inch or more suggests the correction has been lost, along with postural measurements comparing shoulder and hip height and recording how your weight distributes between your left and right foot. Those numbers get compared directly against your post-correction baseline.

Your original correction was calculated from a specific X-ray series (typically nasium, vertex, and lateral cervical views) measured to fractions of a degree. That measured misalignment is what gives the doctor a target and a way to verify success rather than guessing based on how your neck feels or sounds.

a man getting his neck looked at by a dr

How long does it take before a correction starts holding?

Most patients begin holding longer within the first two to six weeks, though it depends on how long the misalignment was present and how much soft tissue adapted around it. Ligaments and postural muscles keep a shape the way an old shoe does, so early on they pull the atlas back toward the familiar position. That is why the first visits sit close together, often every two to four days.

As the tissue adapts, the interval stretches: a few days, then one week, two, four, eight, and eventually twelve weeks or longer between checks. Some long-term patients come in a few times a year and hold the whole way through.

A small pilot study by Bakris and colleagues, published in the Journal of Human Hypertension in 2007, shows the principle from a research angle: participants received one NUCCA atlas correction and were followed for eight weeks with no further adjustments, and the corrected group showed a significantly greater drop in blood pressure than the sham group.

What causes someone to lose a correction?

The usual culprits are mechanical and specific rather than mysterious:

  • Falls, sports contact, or a low-speed car collision
  • Long dental appointments with the mouth held open and the head extended
  • Sleeping in an unfamiliar position or on a couch
  • A hard bout of coughing or vomiting during illness
  • Sustained emotional stress, which raises resting tension in the upper neck muscles

Symptoms usually return within a day or two, though not always in the same form as before. Some people notice headaches first; others notice old hip pain, dizziness, or jaw tension. Those personal early-warning signs are worth tracking, since they tell you when to call rather than waiting for your next scheduled check.

Getting checked at Atlas Chiropractic

Fewer adjustments is not a shortcut. It is what happens when corrections are measured, verified, and left alone once they hold. If you have been going somewhere weekly for years without being told whether anything actually changed, a full NUCCA examination will give you numbers instead of guesses. Reach out to Atlas Chiropractic to schedule a consultation and find out what your spine is holding onto.

Low-Speed Crash, Lasting Effects: How Minor Car Accidents Affect Your Atlas

The most common thing people say when they finally come into Atlas Chiropractic after a fender bender is that the accident was nothing. Parking lot speed, no damage worth claiming, felt fine driving away. Then the headaches start, or the neck stiffness, or the dizziness that shows up when they turn to back out of a driveway. Vehicle damage and occupant injury are two different measurements, and one does not predict the other.

Can a crash under 10 mph really injure your neck?

Yes, and the biomechanics research on this is not new. Studies of rear-end impacts have documented occupant symptoms at changes in velocity as low as roughly 5 mph, because your head does not experience the same acceleration the car does. In a rear impact the head can see acceleration two to two and a half times greater than the vehicle’s, since the seat drives the torso forward while the head is still at rest.

The timeline is the other half of it. The whole injury event unfolds in about 100 to 300 milliseconds. Voluntary muscle reaction time runs slower than that, so the neck muscles you would use to brace arrive after the strain has occurred. Bracing does not help, which is part of why minor collisions catch people off guard.

a person with in injured neck

Why doesn’t the damage to your bumper tell you whether you were hurt?

Because bumpers are engineered to absorb impact without showing it. The federal bumper standard, 49 CFR Part 581, requires passenger car bumpers to withstand low-speed impacts without damage to safety-related components, which means a bumper can do its job perfectly and look untouched while the energy passes through to the occupants.

Modern vehicles are also stiffer than older ones at low speeds. A bumper that crumples absorbs energy. A bumper that rebounds transfers it. Insurers still lean on photographs of undamaged panels as evidence that nobody could have been hurt, which is a claims argument rather than a clinical one.

What actually happens to the atlas in a collision?

The atlas is the top vertebra of the neck, a ring of bone weighing about two ounces that balances a head of roughly 10 to 12 pounds. During the first 50 to 75 milliseconds of a rear impact, the cervical spine briefly forms an S shape, the lower segments extending while the upper segments are still flexed. That is not a motion the neck performs in normal life, and it loads the ligaments around the atlas and axis (C1 and C2) in a direction they are not built to resist.

When those ligaments are strained, the atlas can settle slightly off its normal alignment and stay there. The rest of the body compensates. Head tilt, uneven shoulder height, a functional leg length difference, and altered muscle tone down the spine are the downstream results, and they persist until the alignment is addressed.

Why do symptoms appear days or weeks after the crash?

Inflammation and protective muscle spasm build over the first 24 to 72 hours, and adrenaline at the scene masks a great deal. Some people feel nothing for a week or more.

The Quebec Task Force on Whiplash-Associated Disorders published a grading system in 1995 that is still used clinically. Grade I is neck pain or stiffness with no physical findings, Grade II adds musculoskeletal signs like reduced range of motion or point tenderness, Grade III involves neurological signs, and Grade IV means fracture or dislocation. Most low-speed collision patients land in Grades I and II, which are exactly the categories where imaging looks normal and the complaint gets dismissed.

Persistence is common enough to take seriously. Reviews from the Bone and Joint Decade Task Force on Neck Pain found a substantial portion of people with whiplash-associated disorders still reporting symptoms a year after the collision.

What should you do in the first two weeks after a minor accident?

Get examined and documented early, even if you feel functional. Practical steps:

  • Have a full evaluation within the first week, before symptoms consolidate
  • Write down what you notice daily, including sleep quality and headache timing
  • Keep every record: photos, the police report number, all provider notes
  • Check whether you carry MedPay coverage, which is optional in Indiana and pays medical bills regardless of fault

Indiana’s statute of limitations for personal injury claims is two years from the date of the accident under Indiana Code 34-11-2-4. Gaps between the crash and the first exam also give insurers room to argue your symptoms came from something else, so early documentation protects your health and your position at once.

Some situations need an emergency department first: loss of consciousness, confusion, severe midline neck pain, weakness or numbness in an arm, vision changes, or a head strike while taking a blood thinner.

Getting evaluated at Atlas Chiropractic

A collision that left no mark on your car can still leave your atlas out of position, and the only way to know is to measure it rather than guess from how your neck feels. If you were in an accident recently, however minor it seemed, schedule an examination with Atlas Chiropractic and get a baseline while the timeline still favors you.

Is Upper Cervical Care Safe for Children? A Guide for Fort Wayne Parents from Atlas Chiropractic

Most parents who contact Atlas Chiropractic about their child ask the same thing first: is someone going to twist my kid’s neck? The answer is no, and understanding why gets at what separates upper cervical work from the general picture people carry of chiropractic. Whether it is right for your child is a separate question from whether it is safe, and both deserve a straight answer rather than reassurance.

Is upper cervical chiropractic safe for children?

Reported serious harm from gentle upper cervical care in children is rare, and the small number of documented serious events in the literature involve high-velocity techniques with rotation, not the low-force approach used in upper cervical practice. That distinction matters more than any other detail on this page.

Upper cervical care focuses on the atlas and axis, the top two vertebrae of the neck (C1 and C2). Instead of a broad twisting maneuver, the correction is a light, sustained pressure applied by hand behind the ear, with no rotation of the head and no popping sound. There is nothing for a child to brace against, which is also why most kids do not find it unpleasant.

What does the research actually say about risk?

The honest summary is that serious adverse events are rare in the published record, but the record itself is thin.

A 2015 review in the Journal of Manipulative and Physiological Therapeutics by Todd and colleagues searched the literature for adverse events following manual therapy in infants and children and found 31 cases, 12 of them serious. The serious cases were associated with forceful, high-velocity techniques, and the authors noted that true incidence cannot be calculated because reporting is voluntary and incomplete. An earlier systematic review in Pediatrics (Vohra et al., 2007) reached a similar conclusion and raised a second concern: delayed diagnosis, meaning a child stays in manual care while an underlying medical problem goes unaddressed.

That second risk is the one a good practitioner actively manages, and it is a fair thing to ask about directly.

How is a child’s adjustment different from an adult’s?

Force is scaled to the child, and for young children it is a fraction of what an adult receives. Practitioners commonly describe pediatric contact pressure as similar to what you would use to check whether a tomato is ripe, applied with a fingertip rather than the full hand and body mechanics used on adults.

The examination changes too. A child’s checkup leans on postural observation, symmetry of head tilt and shoulder height, range of motion, and a supine leg length check rather than the detailed measurement series used with adults. Visits are short, and a young child stays clothed and often sits on a parent’s lap.

Will my child need X-rays?

Not necessarily, and any imaging decision should follow the ALARA principle, meaning radiation exposure kept As Low As Reasonably Achievable. Adult upper cervical care usually begins with a precise X-ray series, but the calculation is different for children, and many practitioners work from clinical findings alone or wait until a child is older.

If imaging is recommended, ask what specific question it will answer and what changes if the answer comes back one way or the other. The Image Gently Alliance, a coalition of radiology and pediatric organizations, publishes plain-language guidance for parents on pediatric imaging that is worth reading before you agree to films.

What do parents bring kids in for, and what is the evidence?

The most common reasons are neck stiffness, head tilt, headaches in older children and teens, and posture concerns after a fall, a sports collision, or a car accident. Parents also ask about colic, ear infections, bedwetting, and attention problems.

Evidence for musculoskeletal complaints like neck pain and headache is stronger than evidence for the non-musculoskeletal conditions on that list, where studies are small, mixed, or low quality. Anyone who tells you upper cervical care cures ear infections is going past what the research supports. Expect instead a clear description of what is being measured, what a reasonable trial of care looks like in weeks rather than years, and what would count as no response.

When should you call your pediatrician first?

Some situations belong with a physician before anyone touches your child’s neck. Call your pediatrician, or seek urgent care, for sudden head tilt with fever, neck stiffness with a headache and light sensitivity, any weakness or numbness, a suspected fracture after a significant fall or collision, unexplained weight loss, or a child under a year old with new symptoms you cannot account for.

Upper cervical care sits alongside pediatric medical care. It does not replace well visits, vaccinations, or the evaluation of anything acute.

Talking with Atlas Chiropractic about your child

Ask about training in pediatric care, verify the license through Indiana’s professional licensing lookup, and expect a consultation before any adjustment. If you are a Fort Wayne parent weighing this for your child, reach out to Atlas Chiropractic to schedule a consultation and get your questions answered before deciding anything.

Atlas Chiropractic care

Why Your First NUCCA Adjustment May Hold for Weeks or Months: Insights From Atlas Chiropractic

Patients new to NUCCA care often arrive expecting what they’ve come to associate with chiropractic. A quick visit, a few cracks, schedule the next appointment in a couple of days, repeat. When we explain that their first correction at Atlas Chiropractic may hold for weeks, sometimes months, the reaction is usually some mix of skepticism and relief. How can one gentle adjustment last that long when their previous chiropractor wanted to see them twice a week indefinitely? The answer comes down to how NUCCA approaches the spine, what makes the correction so specific, and why frequency of care is not a measure of quality.

How NUCCA Differs From Conventional Chiropractic

Most chiropractic techniques work segment by segment. The doctor identifies areas of restriction or misalignment along the spine and applies high-velocity adjustments to restore motion. These adjustments often produce the audible pop that patients associate with chiropractic care. Because the corrections target individual segments and the body tends to drift back toward its previous compensation patterns, frequent visits are often needed to maintain results.

NUCCA takes a different approach. The technique focuses on the relationship between the head, the atlas vertebra, and the rest of the spine as a single interconnected system. When the atlas is properly aligned, the rest of the spine tends to follow. The correction is calculated through precise digital imaging that measures the exact position of the atlas in three dimensions, and the adjustment itself is gentle, specific, and designed to restore the head’s balance over the spine.

The result is a correction that addresses the foundational misalignment driving compensations throughout the body, not just one of many symptoms of that misalignment. When the foundation holds, the structure above it stays stable.

Why Holding Matters More Than Adjusting Frequently

The goal of NUCCA care isn’t to adjust you often. It’s to adjust you well and then leave the correction alone so your body can adapt to the new alignment. Every time the atlas is moved, the surrounding muscles, ligaments, and soft tissues need time to settle into the new position. Constant adjusting interferes with that process. The body never gets a chance to stabilize.

This is why NUCCA practitioners check whether you still need an adjustment before performing one. Leg length comparisons, postural analysis, and other assessments help determine if the previous correction is holding. If your alignment is stable, no adjustment is given that visit, regardless of what your appointment was scheduled for. Holding the correction is the point.

What Determines How Long a Correction Lasts

Several factors influence how long your first NUCCA adjustment holds, and understanding them helps explain the variability we see between patients.

The severity and duration of the original misalignment matters significantly. Someone whose atlas shifted recently from a single event, like a fall or minor accident, often holds corrections longer than someone whose misalignment built up over decades of compensation. Older misalignments have created deeper muscular and ligamentous patterns that take more time to release.

Tissue quality plays a role. Patients with healthier muscles, ligaments, and connective tissue tend to hold adjustments longer. Chronic dehydration, poor sleep, high stress, and inflammatory conditions can all reduce how well the body maintains a correction.

Daily habits matter too. Patients who sleep on their stomach, slouch at a desk for ten hours a day, or spend their evenings looking down at a phone are constantly placing stress on the upper cervical spine. These patterns can pull the atlas back out of alignment faster than gentler daily routines.

What You Can Do to Help the Correction Hold

The hours and days immediately after your first adjustment are particularly important. We typically recommend avoiding strenuous activity, heavy lifting, and aggressive exercise for about 48 hours so the soft tissues can settle. Sleeping on your back or side with proper support helps protect the new alignment overnight. Drinking enough water supports tissue health and helps the body adapt.

Avoid getting other adjustments from providers using high-velocity techniques during this period. The forces involved can undo the precise correction NUCCA worked to establish.

What Typical NUCCA Care Looks Like Over Time

A common pattern in NUCCA care involves more frequent visits early on, as the body learns to hold the new alignment, followed by progressively longer gaps between appointments as stability improves. Patients may start with weekly visits for a few weeks, transition to every two or three weeks, then to monthly check-ins, and eventually to maintenance visits every several months.

This pattern reflects the technique working as designed. The goal is to need less care over time, not more. Patients who reach long holding patterns often feel better than they have in years, with corrections lasting for extended periods between visits.

What This Means for Your Care

Walking out of your first NUCCA correction can feel anticlimactic. There was no crack, the adjustment was subtle, and you may not feel dramatically different in the moment. The changes happen gradually as your body adapts to proper alignment over the following days and weeks. That’s the technique doing exactly what it’s supposed to do. If you’ve been dealing with chronic neck pain, headaches, or other symptoms and want to explore whether NUCCA care fits your case, the team at Atlas Chiropractic in Fort Wayne can walk you through what to expect.